EMR vs. EHR vs. PHR: What’s the Difference?
Table of contents
- In Short: EHR vs. EMR vs. PHR
- EHR vs. EMR vs. PHR: Comparison Table
- What Is an Electronic Medical Record (EMR)?
- What Is an Electronic Health Record (EHR)?
- EMR vs. EHR: What Is the Actual Difference?
- What Is a Personal Health Record (PHR)?
- What Is a Patient Portal?
- PHR vs. Patient Portal: Why They Are Not the Same
- How EHRs, EMRs, PHRs, and Patient Portals Work Together
- Interoperability: FHIR, HL7, USCDI, and APIs
- What Does Your Healthcare Organization Actually Need?
- Security and Privacy Considerations
- Common Questions About EMRs, EHRs, PHRs, and Patient Portals
- Is an EMR the same as an EHR?
- Can an EMR exchange data with other systems?
- Is a patient portal part of an EHR?
- Is a PHR covered by HIPAA?
- Can a healthcare organization use an EHR, PHR, and patient portal together?
- Wrapping Up
- Planning an EMR/EHR project?
Healthcare software is full of overlapping terms, and EMR, EHR, and PHR are among the easiest to confuse. All three deal with health information, but they differ in scope, who primarily manages the record, and how the information is used and exchanged.
The distinction between EMR and EHR systems is especially easy to overstate. In practice, healthcare organizations and software vendors often use the terms interchangeably, and a product called an “EMR” may offer capabilities commonly associated with EHRs. The name alone says little about how well a system exchanges data with other providers, laboratories, pharmacies, health information exchanges, or third-party applications.
A personal health record (PHR) introduces a different perspective: it is organized around the individual rather than primarily around a healthcare organization’s clinical workflows. Patient portals are related to these systems but serve another purpose, which we’ll examine separately.
This article explains where the concepts differ, where the boundaries overlap, and how EMRs, EHRs, PHRs, and patient portals fit into a modern healthcare IT environment.
In Short: EHR vs. EMR vs. PHR
A quick way to understand the difference is to look at what each record is designed to do:
EMR — Electronic Medical Record
A digital clinical record primarily created and maintained within a healthcare organization or practice. It supports day-to-day care activities such as documenting encounters, diagnoses, medications, test results, and treatment.
EHR — Electronic Health Record
A broader, longitudinal health record designed to make relevant patient information accessible across providers, care settings, and systems. Data exchange and continuity of information across the patient’s care journey are central to the concept.
PHR — Personal Health Record
A health record primarily managed for or by the individual. A PHR may bring together information from healthcare providers, health apps, connected devices, wearables, and patient-entered data.
EHR vs. EMR vs. PHR: Comparison Table
EMRs, EHRs, and PHRs can contain some of the same health information, but they are organized around different users and workflows. The table below compares the concepts by scope, data sources, interoperability, and the way each record is typically maintained.
To keep the comparison practical, we focus on who typically maintains or manages each type of record. Legal ownership of medical records can vary by jurisdiction and setting.
|
Criterion |
EMR |
EHR |
PHR |
|
What it is |
A digital clinical record primarily used within a healthcare organization or practice |
A broader longitudinal health record designed to support information exchange across providers and care settings |
A health record primarily managed for or by the individual |
|
Primary users |
Clinicians and healthcare staff |
Clinicians and healthcare organizations across care settings |
Patients and, where authorized, caregivers |
|
Primary scope |
Usually one organization, facility, practice, or provider group |
Multiple providers, organizations, or care settings |
The individual’s health information, potentially collected from multiple sources |
|
Who primarily maintains/manages the record |
The healthcare organization or practice |
Healthcare organizations and the health IT systems supporting care across settings |
Primarily the individual and/or the PHR service, depending on the platform |
|
Typical data sources |
Clinical documentation, diagnoses, medications, laboratory results, procedures, and other care data. |
Contributing healthcare providers, laboratories, pharmacies, specialists, hospitals, and health information exchanges |
Healthcare providers, apps, wearables, connected devices, and patient-entered information |
|
Interoperability |
Varies by implementation, cross-organization exchange may require additional integrations |
Information exchange across care settings is a core design objective, although actual interoperability still depends on implementation |
Varies considerably depending on the platform, supported standards, and available integrations |
|
Patient-generated data |
Possible, although often secondary to clinician-generated records |
Commonly supported through portals, connected applications, devices, or other integrations |
Often an important source of information |
|
Typical integrations |
Laboratories, imaging systems, billing, scheduling, pharmacies, APIs, and potentially external health networks |
HIEs, laboratories, pharmacies, payers, public health systems, other providers, and third-party applications |
EHR APIs, health apps, wearables, connected devices, and other consumer health services |
|
Typical use cases |
Clinical documentation and workflows within a healthcare organization |
Care coordination and longitudinal information exchange across healthcare settings |
Personal health management and aggregation of information from multiple sources |
What Is an Electronic Medical Record (EMR)?
An electronic medical record (EMR) is the digital clinical record used within a healthcare organization, practice, or provider group to support everyday care delivery. In practical terms, it is where clinicians document what happens during visits and keep the information they need to manage a patient’s care within that organization.
An EMR may contain:
- Encounter notes and clinical histories
- Diagnoses and problem lists
- Medication and allergy information
- Laboratory and imaging results
- Treatment plans and procedures
- Orders, referrals, and follow-up information.
Its main users are clinicians and other healthcare staff involved in diagnosis, treatment, documentation, and operational workflows. Depending on the product, the same system may also connect clinical activity with scheduling, billing, prescribing, or other practice-management functions.
EMRs are generally more organization-centric than EHRs, but modern platforms can still connect with external healthcare systems when the required interfaces and integrations are in place.
What Is an Electronic Health Record (EHR)?
An electronic health record (EHR) is built around continuity of patient information over time and across care settings. Instead of viewing each encounter as an isolated episode, it brings together relevant information from different parts of the patient’s care journey.
That longitudinal view may include records from primary care, specialists, hospitals, laboratories, pharmacies, and other care participants. As a result, an EHR can give clinicians more context when a patient moves between providers or receives treatment from several organizations. Interoperability is therefore central to the EHR concept: relevant clinical information should be able to move across systems and care settings where appropriate.
Typical EHR capabilities may include clinical documentation, computerized orders, medication management, results review, care coordination, decision support, patient access, and information exchange with external systems. This broader scope makes EHRs particularly relevant where care is distributed across multiple teams or facilities.
Organizations evaluating this type of system should also consider the operational trade-offs involved; our overview of EHR pros and cons looks at those advantages and limitations in more detail.
EMR vs. EHR: What Is the Actual Difference?
The clearest distinction between an EMR and an EHR is the scope the system is designed to support. An EMR is typically centered on clinical work within a particular organization, while an EHR is conceived as a longitudinal record that can support care across different providers and settings.
|
EMR |
EHR |
|
Primarily centered on the clinical workflows of a specific organization or practice |
Designed around a broader, longitudinal view of the patient’s health information |
|
Usually supports documentation and care delivery within that organization |
Accommodates information created across different providers and care settings |
|
External data exchange depends on the platform, implementation, and integrations in place |
Interoperability and continuity of information are more fundamental to the concept |
|
May still connect extensively with laboratories, pharmacies, HIEs, and other systems |
Typically places greater emphasis on exchanging and incorporating information from external sources |
In practice, the boundary is less clear-cut. Vendors and healthcare organizations often use EMR and EHR interchangeably, and systems carrying either label can vary widely in functionality. Organizations should therefore evaluate workflows, interoperability standards, APIs, and the design of EMR/EHR integrations rather than rely on the product name alone.
What Is a Personal Health Record (PHR)?
A personal health record (PHR) puts the individual at the center of record management. Rather than being built primarily around one provider’s clinical workflows, it can bring together health information from several places and make it available in one patient-oriented environment.
Depending on the platform, a PHR may combine:
- Records received from healthcare providers or health plans
- Information from health and wellness apps
- Data from wearables and connected devices
- Medications, allergies, conditions, or other information entered by the individual.
This means a PHR can cover more than formal clinical documentation. Someone might use it to combine provider records with activity, sleep, blood pressure, glucose, or other data collected outside the clinical setting. Some solutions connect directly to healthcare organizations, while others operate as standalone consumer health products. For that reason, it is more useful to think in terms of PHR models and data sources than to define the category through a list of specific products.
The individual also has a more active role in managing the record. Depending on the service, patients may add information themselves, connect external data sources, or decide when certain information is shared with healthcare professionals or other applications.
Privacy note. Whether a PHR is covered by HIPAA depends on who provides the service and their relationship to the individual. Standalone consumer health products may fall under different privacy requirements, which we discuss later in the article.
What Is a Patient Portal?
A patient portal is the patient-facing access layer of a healthcare organization’s digital ecosystem. It commonly connects to an EHR or EMR and gives patients a way to interact with their provider and selected parts of their health information online.
Depending on the organization and platform, patients may use a portal to:
- View test results, visit summaries, medications, and other available records
- Exchange secure messages with care teams
- Schedule or manage appointments
- Request prescription refills
- Complete forms and update certain information
- Review bills and make payments
- Download or share available health documents.
The portal itself is usually an interface rather than the underlying clinical system of record. The EHR or EMR continues to support clinical documentation and care workflows, while the portal exposes selected information and services to the patient.
PHR vs. Patient Portal: Why They Are Not the Same
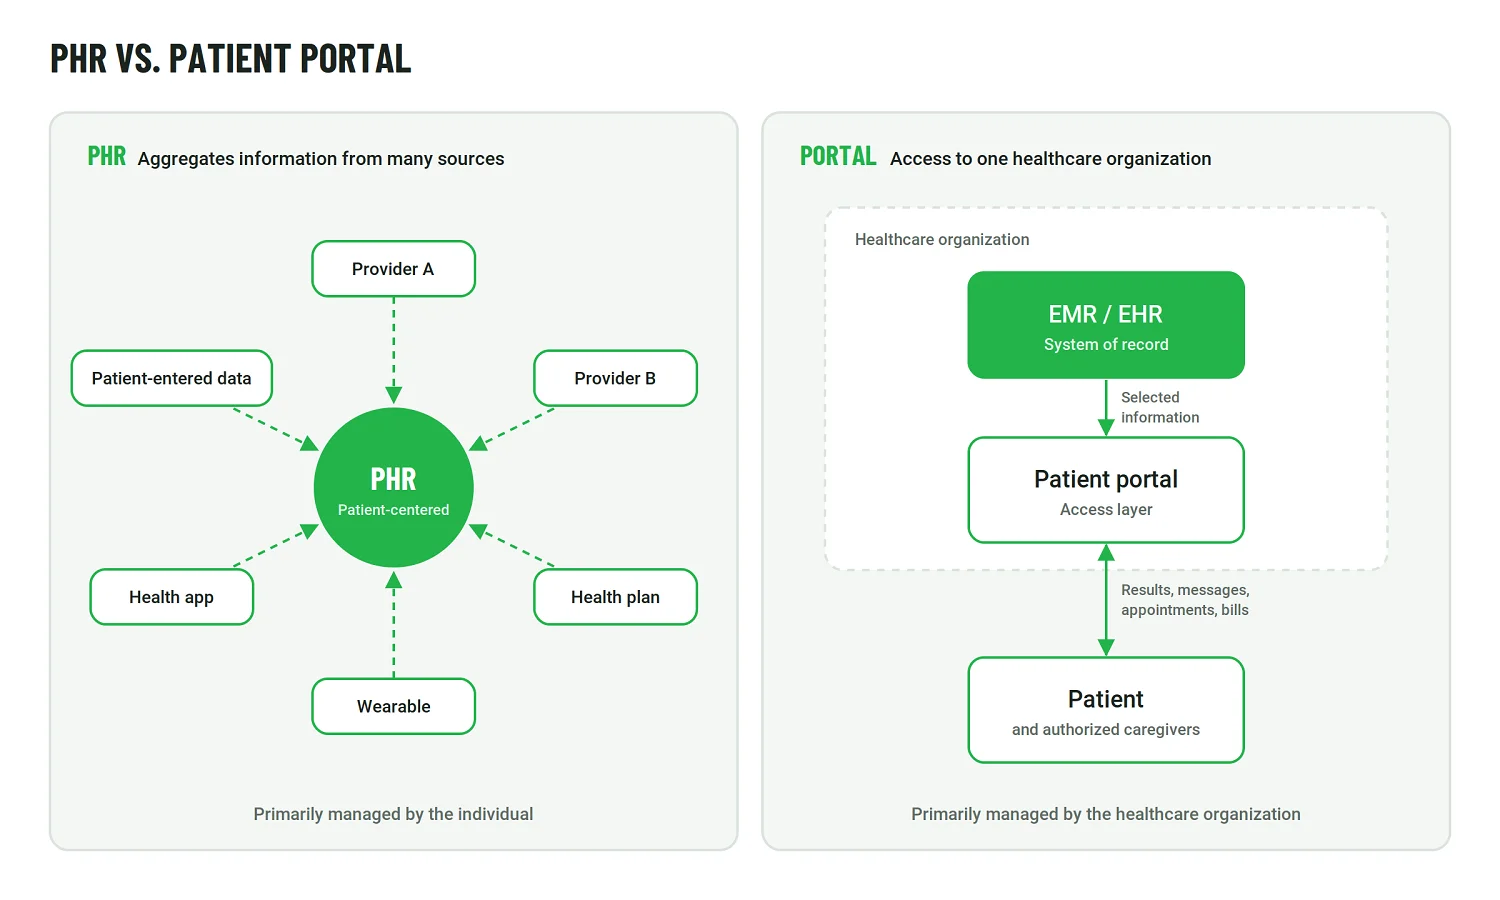
The difference becomes much clearer when you compare what each tool is designed to help the user do. A PHR is oriented toward managing a person’s health information across potentially many sources. A patient portal is primarily a way to access and interact with a particular healthcare organization.
|
Criterion |
PHR |
Patient portal |
|
Primary purpose |
Managing personal health information over time |
Accessing information and interacting with a healthcare provider |
|
Data sources |
Potentially multiple providers, apps, wearables, and connected devices |
Primarily the healthcare organization or organizations connected to the portal |
|
Who primarily manages it |
The individual, often with support from the PHR platform |
The healthcare organization and the platform behind the portal |
|
Data entry |
Patient-entered information plus data imported from connected sources |
Primarily provider/EHR data, with patient-entered information in selected workflows |
|
Main value |
Longitudinal personal health management and aggregation of information |
Access, communication, transactions, and self-service with a provider |
The two can still interact. Information available through a provider may be exported or shared with a patient-controlled health application or PHR, depending on the systems and permissions involved. That connection does not turn the patient portal itself into a PHR.
How EHRs, EMRs, PHRs, and Patient Portals Work Together
In practice, these systems are often parts of the same information flow rather than alternatives that an organization must choose between.
Two simplified paths help show how they can connect:
Provider → EMR/EHR → Patient Portal → Patient
and
EHRs/health apps/wearables → PHR ← patient-entered data
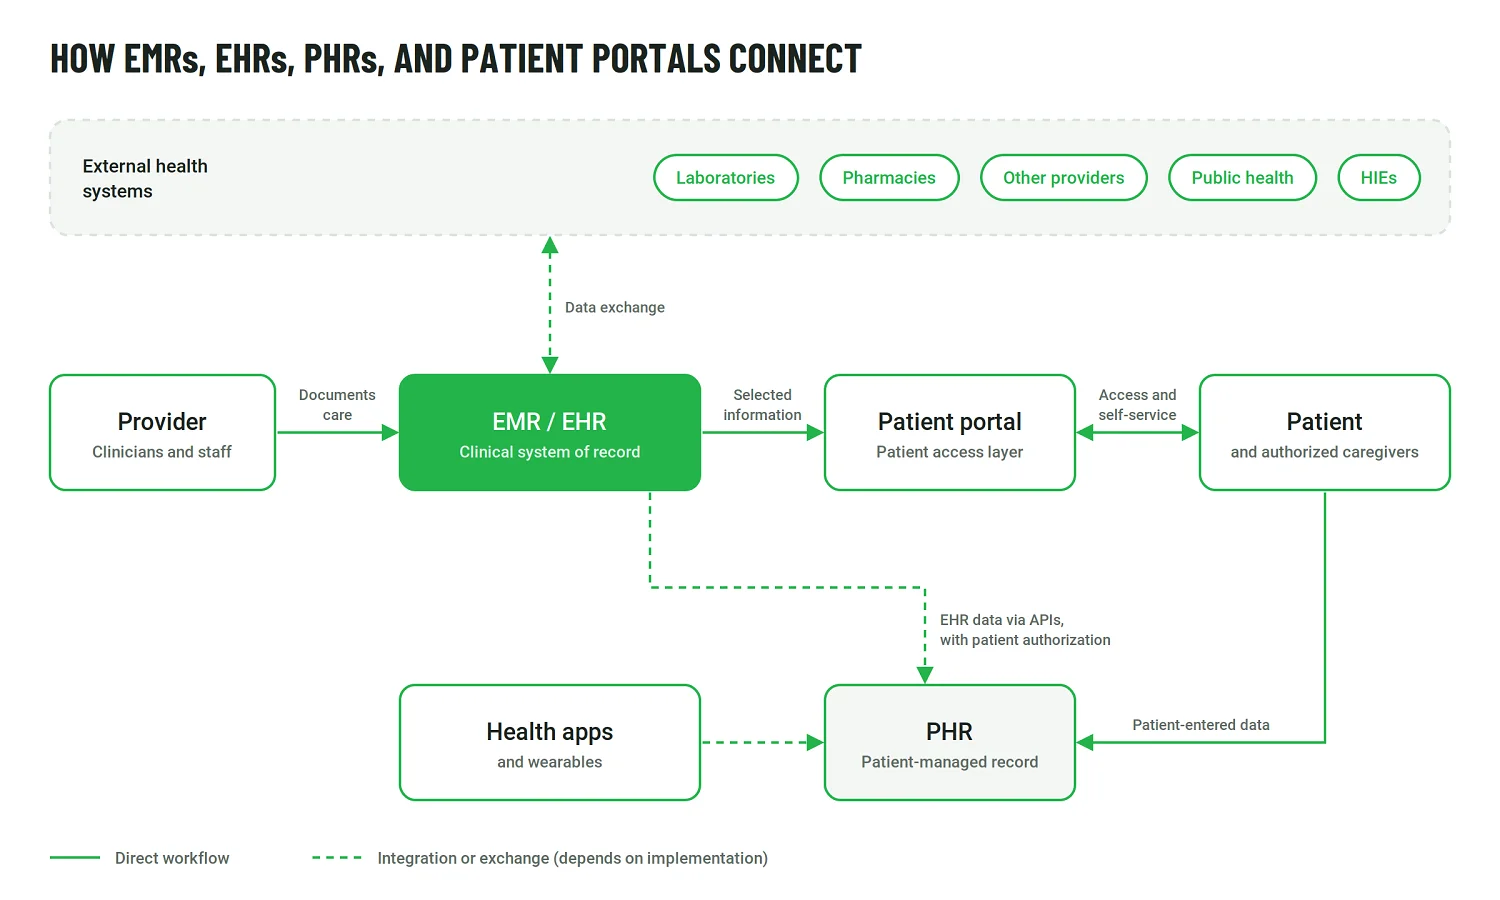
Consider a routine clinical encounter. A physician documents the visit in the organization’s EMR or EHR. Selected information, such as test results, medications, visit summaries, or follow-up instructions, may then become available to the patient through the portal.
With the patient’s authorization and where the necessary integrations are available, some of that information can also move into a PHR or another health application. At the same time, the clinical system may exchange data with laboratories, pharmacies, other providers, public health systems, or a health information exchange.
Interoperability: FHIR, HL7, USCDI, and APIs
Modern healthcare interoperability goes beyond transferring data from one system to another. The receiving system also needs to understand the structure and meaning of that information and, where appropriate, make it available to other authorized applications.
Several standards and frameworks support different parts of this exchange:
- HL7 FHIR (Fast Healthcare Interoperability Resources) provides a standardized framework for exchanging healthcare information electronically and is widely used for API-based integration.
- USCDI (United States Core Data for Interoperability) defines a baseline set of health data classes and elements for interoperable exchange in the US.
- C-CDA (Consolidated Clinical Document Architecture) supports structured clinical documents such as care summaries, consultation notes, and discharge summaries.
- Clinical terminologies such as SNOMED CT and LOINC, alongside ICD and RxNorm, help systems represent clinical concepts, observations, diagnoses, and medications consistently.
- Health information exchanges (HIEs) support data sharing among participating healthcare organizations, while SMART on FHIR provides a standards-based approach for connecting authorized third-party applications to FHIR-enabled systems.
The standards landscape continues to evolve. USCDI v3 became the baseline for the ONC Health IT Certification Program on January 1, 2026, while the 2026 Standards Version Advancement Process (SVAP) approved newer voluntary options, including USCDI v6, C-CDA 5.0, and HL7 FHIR US Core STU 9.0.0.
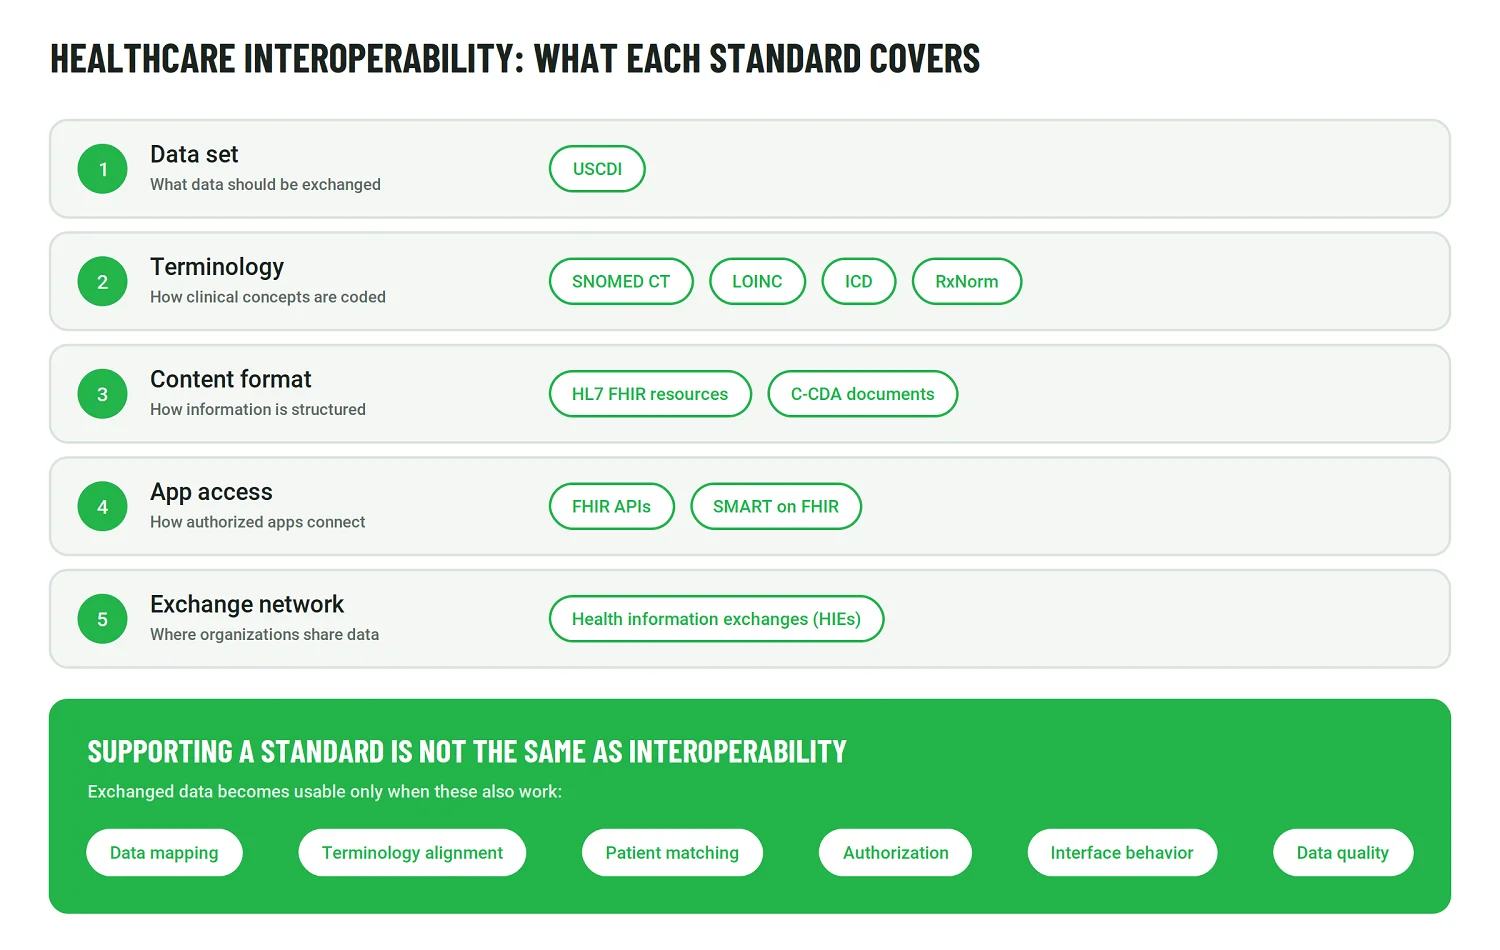
Supporting a standard, however, does not make two systems automatically interoperable. Data mapping, terminology alignment, patient matching, authorization, interface behavior, and data quality still determine whether exchanged information can actually be used.
What Does Your Healthcare Organization Actually Need?
Choosing between an EMR, EHR, PHR, and patient portal is rarely a useful procurement exercise on its own. A better starting point is the problem the organization needs to solve.
- You need a clinical EMR/EHR core when the priority is documenting care and supporting workflows such as diagnoses, medications, orders, results, referrals, and billing. The appropriate scope depends on the organization, its care model, and the systems it needs to connect with. If a new platform is being considered, the decisions involved in building an EHR extend from requirements and architecture to compliance, integrations, testing, and deployment.
- You need stronger interoperability when information has to move reliably across healthcare organizations and systems. In that case, standards support, APIs, data models, and integration architecture become key selection criteria.
- You need a patient portal when patients need secure digital access and self-service capabilities within their relationship with the provider.
- You may need a PHR or consumer health application when users need a patient-controlled health record that can bring together information from multiple sources.
These needs can overlap, so an organization may use several of these components within the same healthcare environment.
Security and Privacy Considerations
Health information handled through an EMR, EHR, PHR, or patient-facing application requires both technical safeguards and a clear understanding of which privacy rules apply.
In the US, the HIPAA Security Rule establishes safeguards for electronic protected health information (ePHI) handled by covered entities and their business associates. Among other requirements, it addresses access control, authentication, audit controls, integrity, and protection of data during transmission.
PHRs and consumer health apps need additional attention because HIPAA coverage depends on the relationship between the application and the healthcare organization. HHS explains that when an individual directs health information to an app that is neither a covered entity nor a business associate, the data is no longer protected by the HIPAA Rules once the app receives it. An application provided by or on behalf of a covered healthcare organization may fall under a different regulatory relationship.
Products outside HIPAA are not necessarily outside privacy regulation. The FTC Health Breach Notification Rule applies to vendors of personal health records and certain related entities that are not covered by HIPAA. The FTC’s 2024 amendments clarified its application to many health apps, connected devices, and similar consumer health technologies.
Regulatory compliance also has to be reflected in the product design. Depending on the system and risk profile, that may include role-based access, strong authentication, detailed audit logs, secure transmission, and careful control of administrative privileges. These measures help limit inappropriate access while giving organizations a reliable record of who viewed, changed, or shared sensitive health information.
Common Questions About EMRs, EHRs, PHRs, and Patient Portals
Is an EMR the same as an EHR?
Not exactly, although the terms are often used interchangeably. An EMR is generally more organization-focused, while an EHR places greater emphasis on longitudinal information across care settings.
Can an EMR exchange data with other systems?
Yes. Modern EMRs can exchange data with external systems through standards-based interfaces, APIs, and other integration mechanisms. The available capabilities depend on the product and implementation.
Is a patient portal part of an EHR?
It can be closely integrated with an EHR, and many EHR platforms include portal functionality, but the concepts are different.
The EHR supports clinical records and healthcare workflows. The patient portal is the patient-facing access layer through which selected information and services are made available.
Is a PHR covered by HIPAA?
Sometimes. A PHR offered by or on behalf of a HIPAA-covered organization may be subject to HIPAA, while a standalone consumer PHR may fall under other privacy requirements.
Can a healthcare organization use an EHR, PHR, and patient portal together?
Yes. They serve different roles and can be integrated within the same healthcare ecosystem. The combination depends on the organization’s clinical, interoperability, and patient-access requirements.
Wrapping Up
EMRs, EHRs, PHRs, and patient portals serve different roles in healthcare IT. Understanding their scope, data flows, interoperability requirements, and privacy boundaries is a better basis for technology decisions than relying on product labels alone.
Planning an EMR/EHR project?
Emerline works with healthcare organizations on EMR/EHR development, integration, modernization, and patient-facing solutions. If you are evaluating an existing healthcare IT environment, planning a new product, or working through interoperability and architecture questions, you can contact Emerline to discuss the project and determine which development approach fits the actual requirements.
Updated on Sep 29, 2026





